- Call : +91 9540210956
- Email: [email protected]
- Artemis Hospital Sector 51 Gurgaon
- 09Am - 5Pm


Ground-Glass Lung Nodules: Follow-Up, Cancer Risk and When Surgery Is Needed
- Home
- Blog Details
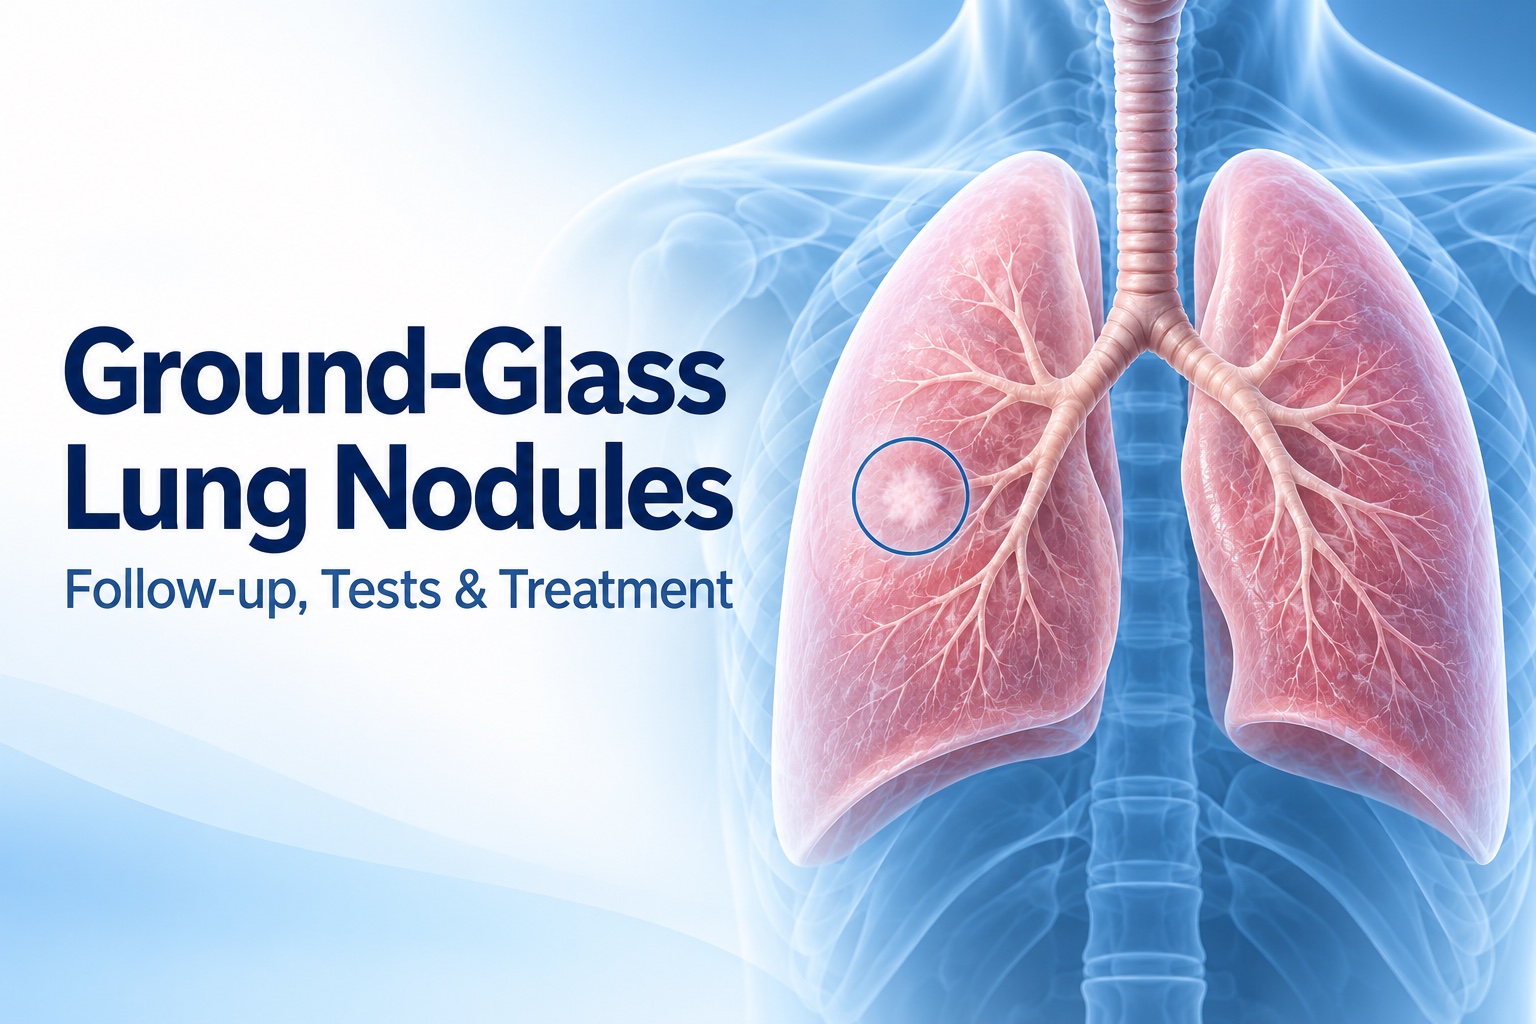
A CT report that mentions a “ground-glass lung nodule” often creates two questions: is it cancer, and why has the doctor suggested another scan instead of removing it immediately? The answer depends on what the nodule looks like, whether it persists and how it changes over time.
Ground glass describes an appearance on CT, not a diagnosis. Some findings disappear, while others remain stable or gradually develop features that need closer investigation. A planned surveillance programme can therefore be an active clinical decision, provided it has a clear timetable and defined reasons to reconsider treatment.
This guide explains pure ground-glass and part-solid nodules, the scope of follow-up guidelines, the limitations of PET and biopsy, and when a thoracic surgical opinion becomes useful.
What Is a Ground-Glass Lung Nodule?
A ground-glass nodule is a localised hazy area in the lung through which underlying vessels or airway margins can still be seen. A solid nodule obscures the structures within it. A part-solid nodule contains both a ground-glass area and a denser solid component.
The term “subsolid” includes pure ground-glass and part-solid nodules. The NCBI Bookshelf chapter on focal lung disease explains these imaging categories. They matter because the interpretation and follow-up of a subsolid nodule differ from those of a completely solid one.
A discrete nodule is also different from a report describing widespread ground-glass opacities throughout the lungs. Before looking up a follow-up schedule, establish which finding your report describes. Our broader lung nodule guide explains the initial assessment.
Does Ground Glass Mean Early Lung Cancer?
No. Transient inflammation or infection can produce a subsolid appearance. Persistent findings can represent several processes, including lesions along the lung adenocarcinoma spectrum. Appearance alone does not provide a microscopic diagnosis.
A 2026 study of ground-glass nodules in a CT screening programme reported a mixture of resolution, stability, benign findings and lung cancer diagnoses. Its selected screening population should not be used to calculate your personal cancer probability. It does show why neither “all ground glass is cancer” nor “ground glass is harmless” is a reliable rule.
Ask whether your finding was present on an older scan, whether it has a solid component, and whether the current appearance suggests a transient cause. These questions are more useful than trying to infer a diagnosis from the word “hazy.”
Why the Solid Component Matters
Doctors assess the whole nodule and any solid portion separately. A pure ground-glass nodule that develops a solid component may need a different discussion from a nodule whose overall diameter has remained unchanged without such a change.
In a prospective Japanese multicentre study published in 2016, 795 patients with 1,229 subsolid nodules were followed for an average of about 4.3 years. Of 1,046 initially pure ground-glass nodules, 56 developed into part-solid nodules. Invasive adenocarcinomas diagnosed in the study were found among the part-solid group.
This was not a study in which every nodule was removed and examined. Its findings do not prove that every pure ground-glass lesion is non-invasive, or that every part-solid nodule is cancer. They support watching the type of change as well as the size.
What Follow-Up Do the Fleischner Guidelines Suggest?
The 2017 Fleischner Society recommendations apply to incidentally detected nodules in adults aged at least 35. They are not a screening protocol and do not apply directly to people with known primary cancer or immunosuppression.
| Finding | Usual guideline approach |
|---|---|
| Pure ground-glass nodule smaller than 6 mm | No routine follow-up for most; selected suspicious or higher-risk findings may be followed |
| Pure ground-glass nodule 6 mm or larger | CT at 6–12 months, then every two years until five years if persistent |
| Part-solid nodule 6 mm or larger, with solid component smaller than 6 mm | CT at 3–6 months; if persistent and unchanged, annual follow-up for five years |
| Growing or concerning solid component | Specialist reassessment rather than automatic continuation of routine surveillance |
Multiple nodules need a separate assessment. Do not use this table to postpone a review already recommended by your treating team.
Why Can the Next Scan Be Months Away?
The interval is chosen to answer a question: does the abnormality resolve, persist or show meaningful change? Repeating imaging too soon may not answer that question, while an overly long interval can be inappropriate for a more suspicious finding.
The American College of Chest Physicians nodule guideline distinguishes subsolid lesions from solid nodules and discusses the role of CT surveillance and patient preferences. Different guideline pathways can therefore produce different intervals. Ask which pathway applies to you and why.
Surveillance should include who orders the scan, who reviews it, how the result reaches you and what change would trigger another investigation. Put the date in your calendar before leaving the appointment. A planned interval is different from a missed appointment or an unresolved referral.
How Do Doctors Decide Whether a Nodule Has Grown?
Reliable comparison needs the original CT images, not just the measurements copied into two reports. Differences in scan technique, reconstruction and measurement can complicate an apparent small change.
The Fleischner Society statement on nodule measurement addresses how nodules should be measured and changes assessed. For a part-solid lesion, the solid portion needs attention in addition to the total dimensions.
Bring older scans in the format the clinic requests. A useful question is: “Is this a confirmed change on comparable images, and has the solid component changed?” That is more informative than assuming that a small difference between printed numbers means progression.
Does Stability for Five Years End the Discussion?
Five years is an important point in commonly used surveillance pathways, but it is not a biological guarantee that no subsolid nodule can ever change afterwards.
A CHEST study published in 2025 examined long-term behaviour of screening-detected pure ground-glass nodules and reported growth in some nodules even after ten years of stability. This observational evidence does not establish that everyone needs lifelong annual CT.
At the end of planned surveillance, ask whether to stop, lengthen the interval or continue selected follow-up. The discussion should consider the nodule history, your health, whether treatment would be appropriate if change occurred, and the burden of additional scans.
Why a Negative PET-CT May Not Settle the Diagnosis
FDG PET detects metabolic activity, but small or low-cell-density tumors may not show uptake clearly above background. Some lepidic and mucinous adenocarcinomas can be relatively low-uptake lesions.
The joint EANM/SNMMI/ESTRO lung cancer PET recommendations explain these limitations. A reassuring PET result must therefore be considered alongside the CT appearance rather than used to dismiss a suspicious subsolid lesion.
PET may still help answer a different question in an appropriate case, such as assessing other suspicious findings. Ask what the scan is intended to establish. Our PET-CT interpretation guide explains why both positive and negative results require context.
When Is a Biopsy Useful?
A biopsy can establish a tissue diagnosis, but the team first considers whether the target can be sampled reliably and whether the result would change management. Small or technically difficult lesions may not yield a definitive sample.
RadiologyInfo's lung biopsy guide describes image-guided sampling, its limitations and risks such as bleeding or pneumothorax. A nondiagnostic result is not the same as a confirmed benign diagnosis.
Before agreeing to a procedure, ask what happens after each possible result: malignant, specifically benign, or insufficient. The American College of Radiology guidance on indeterminate nodules also discusses continued surveillance or repeat sampling when concern remains after a nondiagnostic biopsy.
When Might Surgery Be Discussed?
Persistent suspicious change can bring a thoracic surgeon into the decision. If treatment is appropriate, the amount of lung removed depends on the lesion, location, staging and breathing reserve. Options can include a wedge resection, anatomical segmentectomy or lobectomy.
The National Cancer Institute's treatment guide explains these operations and why treatment is individualised. Our segmentectomy versus lobectomy article covers the trade-offs in more detail.
In the JCOG1211 trial published in 2023, selected patients with ground-glass-dominant lung cancer up to 3 cm underwent segmentectomy with specified lymph node assessment. Five-year relapse-free survival was 98.0% (95% confidence interval 95.9–99.1%). This was a single-arm trial in a carefully selected group. It does not show that every ground-glass nodule needs surgery or that segmentectomy suits every lesion.
Questions That Make the Consultation More Useful
- Is this a pure ground-glass nodule, a part-solid nodule or a different pattern?
- What are the total size and the size of any solid component?
- Is it new, persistent or changing compared with the original images?
- Which guideline or clinical reason supports the proposed interval?
- Would PET or biopsy answer a useful question in my case?
- What specific finding would make you recommend surgery?
- Who will arrange and review the next scan?
For example, a stable pure ground-glass lesion and a changing part-solid lesion should not be treated as equivalent simply because both reports mention the same overall diameter. Ask the reviewer to explain the feature driving the recommendation.
Frequently Asked Questions
Does a ground-glass nodule mean I have pneumonia?
Not necessarily. The term describes appearance, and different causes are possible. Ask what clinical evidence supports infection before assuming a course of treatment resolves the finding.
Can I ignore it because I have never smoked?
No. Follow the plan based on your full assessment. Smoking history is useful information but does not replace review of a scan finding.
Should every ground-glass nodule be removed quickly?
No. The decision should balance the reasons for concern against the risks and consequences of investigation or treatment. Ask for a clear explanation of why surveillance or intervention is proposed.
Can I compare my result with someone else's online?
Only very cautiously. Their nodule type, scan history and clinical situation may differ. Bring your questions to a clinician who can review your images.
Arranging a Thoracic Surgical Opinion
If a nodule is persistent, changing or has prompted a recommendation for surgery, book a consultation with Dr. Parveen Yadav to discuss the images and options. Bring prior scans, reports and any biopsy results so the consultation can address the actual decision rather than a single report phrase.
Selected Research and Guidelines
- Fleischner Society, Radiology, 2017: incidental nodule follow-up with defined exclusions.
- Kakinuma and colleagues, Journal of Thoracic Oncology, 2016: prospective observation of subsolid nodule evolution.
- CHEST, 2025: late growth in some long-stable screening-detected pure ground-glass nodules.
- JCOG1211, Lancet Respiratory Medicine, 2023: segmentectomy outcomes in selected ground-glass-dominant cancers.

Dr. Parveen Yadav
18+ Yrs Exp | 5,700+ Thoracic & Robotic Cancer Surgeries
Dr. Parveen Yadav is a Director and Senior Consultant in Thoracic and Surgical Oncology, specializing in minimally invasive and robotic lung and esophageal surgeries, with advanced training from AIIMS and Tata Memorial Hospital.
View Full ProfileRecent Posts
Thymectomy for Myasthenia Gravis: Who Benefits, Surgery and Recovery
- Dr. Parveen Yadav
- Oct 25, 2026

Lung Function Tests Before Lung Surgery: FEV1, DLCO and Fitness Explained
- Dr. Parveen Yadav
- Oct 17, 2026
Does a Positive PET-CT Always Mean Lung Cancer?
- Dr. Parveen Yadav
- Oct 14, 2026
Chest Drain After Lung Surgery: Care, Removal and Recovery
- Dr. Parveen Yadav
- Oct 10, 2026
Related Posts
Does a Positive PET-CT Always Mean Lung Cancer?
A positive PET-CT does not always mean lung cancer. Learn what FDG uptake means, why inflammation can appear and when EBUS or biopsy may be needed.
- Read More
- Oct, 14 2026
EBUS Biopsy: What to Expect and How It Helps Stage Lung Cancer
Learn why EBUS biopsy is used to sample chest lymph nodes, how to prepare, what recovery involves and how results help guide lung cancer treatment.
- Read More
- Oct, 06 2026
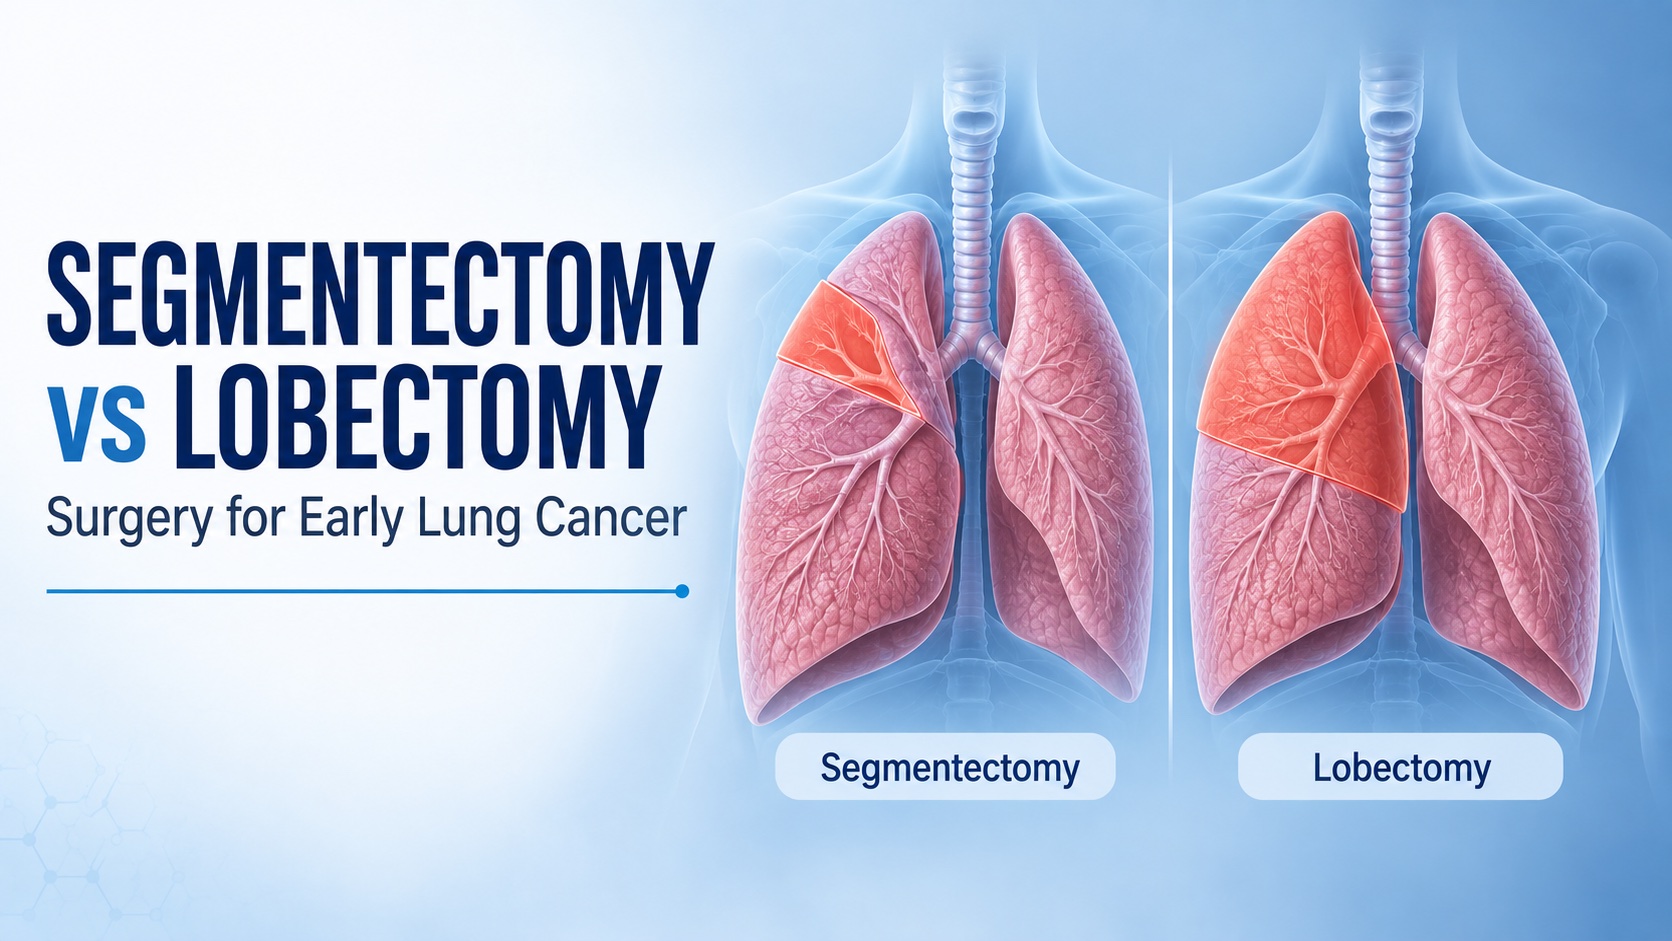
Segmentectomy vs Lobectomy: Choosing Surgery for Early Lung Cancer
Compare segmentectomy and lobectomy for early lung cancer: who may suit lung-sparing surgery, why lymph nodes matter, and what to ask your thoracic surgeon.
- Read More
- Sep, 20 2026
Copyright 2026 © Dr .Parveen Yadav all rights reserved.
Proudly Scaled by Public Media Solution!